


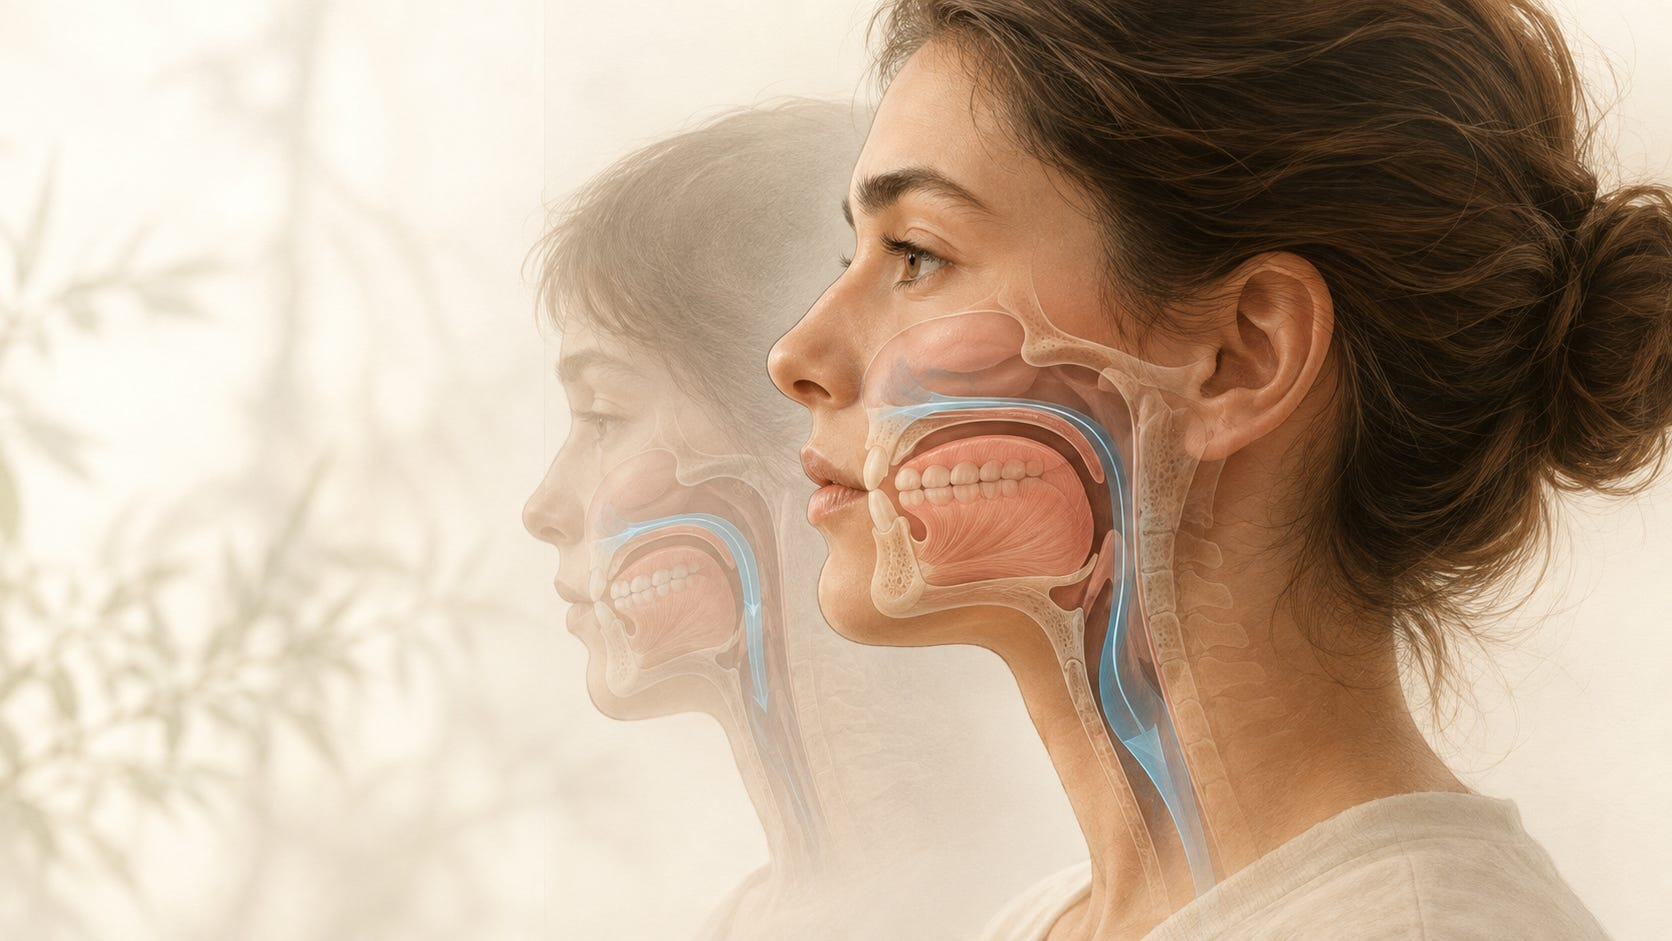
One of the most important questions a patient can ask me is also one of the hardest to answer: “How did I get here?” Sometimes the question comes from someone who snores or has been diagnosed with sleep apnea or upper airway resistance syndrome. Other times, it comes from a person who wakes with headaches, grinds their teeth, or feels exhausted despite spending what should be enough time in bed. They may arrive expecting a conversation about one particular symptom, but the history behind it often gives us more to consider.
By the time we meet, many of these patients have already received years of care. They may have had braces, teeth removed, a night guard made, or a CPAP prescribed. Each treatment may have been reasonable, and some may remain essential. Yet understanding how to manage a problem is different from understanding how it developed. Straightening the teeth does not necessarily explain why there was too little room for them, just as protecting worn teeth does not explain why someone is clenching or grinding.
That distinction has become increasingly important to the way I think about dentistry. The more I have studied airway health, facial growth, nutrition, oral function, and sleep, the harder it has become to view these as entirely separate subjects. Teeth develop within jaws that also provide space for the tongue and help form the structures through which we breathe. What happens in one part of that system may influence another, even when the connection is not immediately apparent during a routine dental examination.
The airway itself develops within a growing face, where genetics interact with breathing patterns, muscle function, feeding, chewing, oral posture, and nasal obstruction. This does not mean that every person with crooked teeth will develop sleep apnea, or that everyone who snores has an underdeveloped jaw. Sleep-disordered breathing can involve the tonsils and adenoids, body weight, neuromuscular tone, nasal obstruction, craniofacial anatomy, and other medical conditions. Oral and facial development belong within that larger picture, not in place of it. To understand the symptoms we see in adulthood, we sometimes need to ask how the entire breathing system developed.
What Weston Price was trying to understand
My interest in this question leads me back to the work of Dr. Weston Price, a Cleveland dentist who traveled to traditional communities around the world. In the Arctic, Australia, the South Pacific, Africa, and other regions, he observed people whose traditional diets had not yet been fully displaced by industrialized Western food. He was interested in tooth decay, but his photographs and observations also documented facial form, dental-arch development, tooth alignment, and the room available for the teeth.
Price compared people eating traditional diets with members of the same communities who had begun consuming more refined flour, sugar, canned goods, and other imported foods. Those observations became the foundation of Nutrition and Physical Degeneration, a book that has influenced generations of biological dentists and other health professionals interested in nutrition. Its enduring value lies partly in the question it raises: why might different living conditions be associated with different patterns of dental and facial development?
We need to be careful about what his work can establish. Price produced an observational field record, not a modern controlled clinical trial. He did not have sleep laboratories, genetic testing, cone-beam imaging, or the diagnostic tools available today, and photographs of broad smiles cannot prove that a population was free from sleep apnea. His observations can encourage investigation without serving as the final answer to every question they raise.
More recent anthropological research has also identified differences in lower-jaw form associated with how populations obtained their food. In one global analysis, mandibular shape reflected differences between agricultural and hunter-gatherer populations more strongly than neutral genetic relationships alone would predict. That finding does not allow us to attribute jaw development to one food or habit, but it supports taking the environment seriously. Genes matter, and so do the conditions in which growth occurs.
Modern food changed more than nutrition
When people hear the phrase industrialized food, they usually think about ingredients: sugar, refined flour, additives, preservatives, and products that bear little resemblance to the plants or animals from which they came. Those nutritional questions deserve attention, but they are only part of the change. Food has also become easier to consume, often requiring much less work from the mouth.
We can drink a meal, squeeze it from a pouch, or eat something that nearly dissolves before we have begun chewing. Grains are finely milled, fruits are blended, meats are softened, and many snacks are designed to be easy to eat. Even foods marketed as healthy may provide very little resistance. A developing child can receive calories while having relatively few opportunities to use the muscles of chewing.
Bone and muscle are living tissues that respond to use. We readily accept this elsewhere in the body: appropriate loading helps maintain the skeleton, while prolonged disuse can weaken both bone and muscle. Research in animals shows that reduced chewing demand can affect jaw-bone metabolism, muscle function, and aspects of upper- and lower-jaw development. Human anthropology points in a similar direction, although it cannot cleanly separate food texture from all the other differences in genetics, culture, health, and environment.
The practical lesson is not that a particular chewy food will guarantee broad jaws or prevent sleep apnea. Nor should we conclude that cooking or processing food is inherently harmful; cooking can make many foods safer and more digestible. Rather, a growing mouth needs appropriate opportunities to develop its function. When nearly everything a child eats is soft, blended, or puréed, it is reasonable to consider whether safe, age-appropriate chewing experiences are receiving enough attention alongside nutritional quality.
Development begins before the adult teeth arrive
By the time crowded permanent teeth become visible, the developmental story has already been unfolding for years. Its earliest chapters include feeding, swallowing, breathing, oral posture, and the eventual transition to solid foods. These activities do more than accomplish an immediate task. They involve the muscles and movements of a mouth that is still learning to function while the face grows around it.
Breastfeeding, for example, requires coordination among the tongue, lips, cheeks, jaw, swallowing reflex, and breathing. Studies have found associations between longer breastfeeding and broader primary dental arches or lower odds of certain bite problems, including posterior crossbite. The evidence has limitations, and feeding history is never the only influence on development. Even so, it gives us reason to think about feeding as a functional process rather than simply a way to deliver milk.
That perspective should support families, not make them feel judged. Breastfeeding may be difficult or impossible because of prematurity, maternal medical complications, limited milk supply, difficulty latching, poor coordination, restricted tongue mobility, or other challenges. Bottle-feeding does not determine a child’s developmental future, and breastfeeding cannot guarantee that everything will develop ideally. What matters is recognizing when feeding is not working well and helping the family obtain appropriate support, whether from a lactation professional, pediatrician, feeding specialist, dentist, or another qualified provider.
The same thoughtfulness belongs in the transition to solid food. Children should not be pushed toward textures they are not physically or neurologically ready to manage. As their abilities develop, however, they need safe, supervised opportunities to explore foods and practice chewing rather than remain indefinitely on a diet composed almost entirely of soft substances. The aim is not allegiance to a particular feeding philosophy. It is to help each child develop healthy function at an appropriate pace.
The tongue is a quiet architect
Most people notice their tongue when they speak, swallow, taste something, or accidentally bite it. They rarely think about where it rests during the much larger portion of the day when none of those activities is happening. Yet its resting position and movement are part of the muscular environment surrounding the teeth. Teeth do not erupt into empty space; they develop among the tongue, lips, and cheeks, whose forces help influence their position.
When that function is balanced, it helps provide a stable environment for the dental arches. A tongue that rests low, pushes forward during swallowing, has restricted mobility, or cannot comfortably occupy the palate may be part of a different pattern. Research supports associations between tongue position or mobility and dental-arch form, but it would be a mistake to make the tongue responsible for every narrow arch or crooked tooth. Genetics, tooth size, nasal obstruction, prolonged oral habits, skeletal relationships, and early tooth loss can also contribute.
The connection becomes easier to understand when we remember that the roof of the mouth is also the floor of the nose. The upper jaw, or maxilla, helps form both spaces, so oral and nasal development are not entirely separate subjects. When a child cannot breathe comfortably through the nose, opening the mouth may become a necessary compensation. The tongue may then rest lower as the mouth takes on a greater role in breathing.
Over time, breathing pattern, oral posture, muscle function, and facial growth may influence one another. Systematic reviews have found associations between chronic mouth breathing and differences in dentofacial development, although the relationship can operate in both directions: nasal obstruction may change oral posture, while craniofacial anatomy may also make breathing more difficult. That is why telling a child to close their mouth may miss the problem. Before treating the open mouth as a habit to correct, we need to consider whether the child can breathe comfortably through the nose.
Common is not the same as ideal
Crowded teeth, braces, wisdom-tooth removal, and long-term retainers are familiar enough that we tend to accept them as ordinary features of growing up. Familiarity, however, can make us less curious about the patterns in front of us. A child’s tightly arranged baby teeth may look beautiful, yet some spacing in the primary dentition can be a favorable sign that room is developing for the permanent teeth to come.
That does not make spacing a reliable forecast on its own. A lack of space between baby teeth does not guarantee future crowding, and visible spaces cannot promise an uncomplicated transition to permanent teeth. Longitudinal research suggests that primary-tooth spacing provides useful information, but it remains one part of the developmental picture. The same is true of a crossbite, a narrow and high palate, chronic congestion, difficulty elevating the tongue, or a persistently open mouth. These observations invite closer attention; they do not establish a diagnosis by themselves.
I am part of this story myself. There was not enough room for my wisdom teeth, so I have 28 teeth rather than the 32 that developed. For a long time, I accepted that as simply the way my mouth was made. Today, I am more interested in why so many people develop teeth for which there is inadequate room. Asking that question does not mean that every extraction was a mistake. Removing a tooth can be entirely appropriate when keeping it would create infection, damage, instability, or another serious problem. We can respect the treatment decision while remaining curious about the developmental circumstances that made it necessary.
Straight teeth are not the entire goal
Arranging teeth into an attractive, functional bite is an important goal. People deserve teeth they can clean, use comfortably, and feel confident showing. But alignment is not the only thing I want to understand when evaluating a patient. I also want to know whether the upper arch is narrow, whether there is room for the tongue, and whether the person can breathe comfortably through the nose.
Sleep history and previous treatment add context to that examination. Snoring, clenching, grinding, a crossbite, or teeth that have shifted after orthodontic care may warrant further questions, particularly when the patient also reports waking unrefreshed. None of these observations replaces an orthodontic diagnosis or establishes an airway disorder. Together, however, they help us consider the teeth within the system in which they function. An airway-conscious plan should take account of the jaws, tongue space, breathing pattern, growth stage, and sleep history rather than approach alignment as an isolated cosmetic concern.
This broader view also requires restraint. Not every crowded mouth needs expansion, extraction is not always wrong, and expansion alone should not be presented as a cure for sleep apnea. Controlled evidence for rapid maxillary expansion as a stand-alone treatment for pediatric obstructive sleep apnea remains limited and inconsistent. Decisions need to reflect the individual’s anatomy, diagnosis, age, growth, and wider medical circumstances. Including the airway in treatment planning should make that planning more thoughtful, not become a reason to prescribe the same appliance to everyone.
What this means for adults
Adults sometimes hear about childhood development and wonder what any of it can offer them now. We cannot return to infancy and change how we were fed, nor can we repeat the years when our faces were growing. Understanding the developmental pathway is not an exercise in regret. Its value is in helping us recognize which questions may still matter.
An adult who wakes with a dry mouth, struggles to breathe comfortably through the nose, or has been told they snore, gasp, or stop breathing during sleep has information worth sharing. Morning headaches, persistent exhaustion, teeth that are becoming shorter or damaged, a crowded-feeling tongue, and changes after orthodontic treatment may also belong in the conversation. Each can have more than one explanation. Clenching, fatigue, headaches, and dental wear do not prove that someone has sleep apnea, but a pattern of several concerns may justify looking beyond the most obvious symptom.
The appropriate evaluation depends on that pattern. It may involve a dentist, physician, sleep specialist, ear-nose-and-throat physician, orthodontist, or myofunctional therapist, with each contributing within their area of expertise. A dentist can identify risks and observations that deserve further attention, but a dental examination alone does not diagnose sleep apnea. When sleep-disordered breathing is suspected, medical evaluation and, when appropriate, an overnight sleep study are important parts of responsible care.
What this means for parents
For parents, this information should encourage observation rather than fear. A single crowded tooth does not mean a child will develop sleep apnea, and snoring for a few nights during a cold is different from a persistent pattern when the child is otherwise healthy. Feeding difficulties also have many possible explanations. Not every problem is caused by a tongue tie, and not every visible tongue restriction requires surgery.
What deserves attention is a pattern that continues. A child who regularly sleeps with an open mouth, struggles to breathe through the nose, snores when healthy, or sleeps restlessly may need a closer look. Heavy grinding, morning headaches, a crossbite, or a developing narrow arch may add useful context. The American Academy of Pediatric Dentistry recognizes mouth breathing, frequent snoring, restless sleep, morning headaches, attention concerns, and witnessed breathing pauses among signs that may warrant screening. In otherwise healthy children, enlarged tonsils and adenoids remain major causes of upper-airway narrowing, making collaboration with pediatric and ear-nose-and-throat providers particularly important.
Noticing something early does not automatically mean treating it early. Sometimes the right next step is monitoring growth and function. In other circumstances, it may be allergy care, feeding support, an ENT evaluation, myofunctional therapy, orthodontic guidance, or a sleep study. The purpose of paying attention is not to place every child into treatment. It is to give families a better chance of understanding a persistent concern before it has been dismissed as something the child will simply outgrow.
How did we get here?
There is no single explanation for crowded teeth, narrow arches, mouth breathing, snoring, and sleep apnea. These problems did not emerge from one food, one parenting decision, one orthodontic philosophy, or one genetic change. They reflect interactions between biology and the conditions of modern life, with different influences carrying different weight in each person.
As food became easier to consume, many mouths had less work to do. At the same time, nasal obstruction and feeding difficulties were not always considered in relation to oral function, while crowded teeth could be treated without much discussion of the surrounding developmental picture. Snoring might be accepted as an ordinary family trait, and worn teeth protected without fully investigating the reasons for the wear. The treatments themselves could still be useful. What was sometimes missing was a conversation connecting the observations.
I believe biological dentistry asks us to make room for that conversation. A crowded tooth, an open mouth during sleep, unusual dental wear, or persistent exhaustion does not tell us everything we need to know. Each may, however, offer a reason to look beyond the immediate complaint and ask what else is happening. Curiosity is useful when it leads to careful examination and appropriate collaboration rather than a predetermined explanation.
The mouth participates in eating, breathing, sleeping, and growth, and its condition can help us understand more than the teeth alone. When we take that broader view, “How did I get here?” becomes a practical question rather than an exercise in looking backward. It helps us decide what deserves attention now, what we still need to understand, and how to make the next step in care a more informed one.
Dr. John Johnson, DDS
Midwest BioHealth
The Johnson Papers